
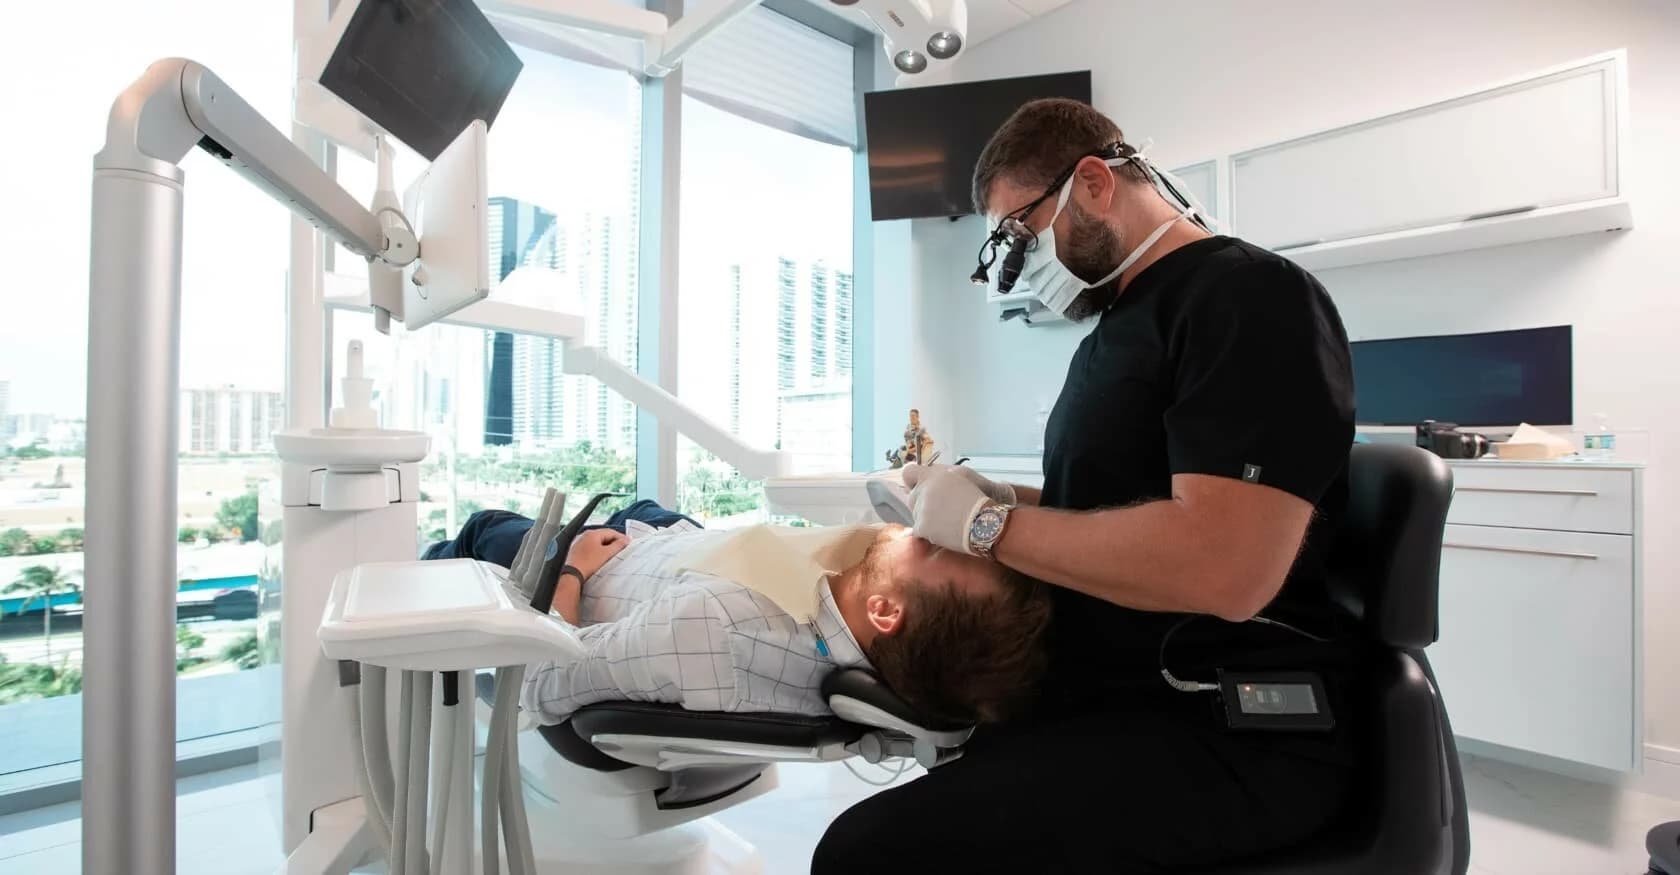
A periodontist is a dentist whose additional training is the tissue that holds teeth and implants: gum, ligament, and bone. The work includes diagnosis, non-surgical treatment such as scaling and root planing when that is indicated, surgery when the tissue problem is beyond what non-surgical care can reach, and the long maintenance that follows either one. It is not a cosmetic specialty that happens to see gums.
Bleeding on brushing, a tooth that feels loose, recession that is advancing, or pus at the gum line are reasons to be examined. They are not, by themselves, a prescription for surgery. Many people are treated and then maintained without an operation. Some need a graft, a pocket procedure, or care around an implant. The examination, including measurements and a radiograph when bone level is the question, is what sorts those groups.
Restorative plans depend on this tissue. A crown, a veneer, or a bridge on a tooth with untreated inflammation is a restoration sitting on a moving foundation. Implants fail more quietly when the tissue around them is ignored after the surgery photographs are done. The periodontist and the dentist placing the teeth need one sequence, not two competing ones.
Not every recession needs a graft, and not every loose tooth can be saved by treatment of the gum. The useful visit ends with a named condition, a first step that is proportionate, and a statement of what maintenance will be required if the tooth or the implant stays. Referral is part of ordinary care when the case needs that training. It is not a verdict that the tooth is being given up.











